

Funding Federations – The Accountable Care Conundrum

You will need to bear with me this week as I try and explain why the funding of GP federations is a critical issue for emerging accountable care systems, because moving to a new non-legislated system is (unsurprisingly) complicated.

Let’s start at the beginning. The principle behind accountable care is one of providers working in partnership with each other to redesign services to improve outcomes. By the way, if “accountable care” does become “integrated care” (or some such) in the next few months, it won’t change anything other than introduce a new set of terms for exactly the same thing – it is simply the price (in my view acceptable) we have to pay for non-legislated reform.

For accountable care to work, one of these providers has to be general practice. In an accountable care system/partnership/organisation (delete as locally appropriate) general practice needs to work in partnership with other local providers. The whole concept builds on the registered list of general practice, and of providing services that are joined together and tailored to meet local needs.

But there are lots of GP practices. Too many for local providers to all build a relationship with each of them individually. As a result, someone has to act on behalf of practices. Partnership between general practice and the rest of the system can’t work without this.

Who, then, should take on this role for practices? Well it can’t be the CCG because they have been established to represent the needs of their local population, not of GP practices as providers. LMCs? The main problem here is that practices need someone to partner on their behalf with the rest of the system. While LMCs are good at representing and articulating the needs of practices, partnership has not historically been a strength. They are also often perceived more as a trade union by other NHS providers. So while in theory LMCs are an option, the reality is without exceptional leadership they are not. Which leaves GP federations (in the absence of a local super-practice) as the best vehicle to enable general practice and the rest of the system to partner with each other.

GP federations are experiencing something of a resurgence at present, as practices seek to gain the benefits of working at scale without formally merging. But one of their challenges, as anyone working within a developing federation will know, is that they don’t have any money. The delivery of some services will create a small margin, but this is rarely enough to fund enough more than a skeleton management team.

Here we (at last) come to the crux of the problem. The system needs GP federations to ensure general practice are part of the provider partnership that underpins accountable care. But partnership working and the building of effective relationships takes time, which someone has to pay for. For GP federations the task is doubly difficult, because at the same time as creating new relationships they have to ensure they have a mandate from their practices and keep them on board with any agreements they make. How can the leaders of GP federations find time for this? Should they do it out of goodwill, and effectively pay for it out of their own pocket by giving their time for free? Should the host practices of the emergent GP leaders bear the cost? Or do we expect the member practices of the federation to contribute the ongoing cost of federation leaders both attending system wide meetings and reporting back to them as the accountable care model develops?

None of these are realistic. So the conundrum is how can federations and those representing general practice be funded to ensure that accountable care systems develop to include general practice?

Answers on a postcard. If this conundrum has been solved in your area I would love to hear how. Email me at ben@ockham.healthcare. Next week I will share the responses (if there are any!) and attempt to consider what mechanisms might be available to find a way through this thorny issue.

What does “being resilient” mean?

The letter I had been waiting for dropped through the letterbox. I had been an “A” student right through school, and my sights were now firmly set on Oxford University. The interviews had been hard to read, but seemed to go ok. I opened the letter. “Thank you for applying to Oxford. After careful consideration it has not been possible to offer you a place”.

I didn’t take it very well. Maybe we are less resilient when we are younger. My (somewhat sulky) response was to decide university wasn’t for me, and I headed off to do voluntary work (“something that mattered!”) instead.

A key part of resilience is described by Bruce Cryer and his colleagues at HeartMath as “releasing the emotional grip” that stress has on us. In their 2003 Harvard Business Review article they describe how to do this, essentially by using techniques to accept the current situation and to develop a new perspective centred on what actions you can take to change the situation.

It took me a long time to do this. After my rejection, I actually did well in my A-Levels, but the following year refused to apply to Oxford again on principle (the principle of, “if they don’t want me, I don’t want them”). I was hanging on to the pain of rejection instead of thinking positively about the future.

Changing our own mindset that things need to and can be different is at the heart of resilience. I think this is the hardest part. In the end, I was sat down by an individual who had become something of a mentor to me. He laid out some different options of what my future might look like. One involved going to Oxford. It did look like the most attractive path… Something seemed to click inside me. It might have taken 18 months(!), but finally I could accept it was me who hadn’t been ready for Oxford (and not vice versa) and I decided to swallow my pride and reapply.

While tenacity and perseverance are key parts of resilience, it is adaptability, and the ability to change mindset, that are more important. Blockbuster Video, Borders Books, Kodak (and many others) kept going for as long as they could when things were tough, but they did not adapt to the new world and the changed environment around them, and ultimately were not able to survive.

I recently had a conversation with Dr Mike Holmes, the newly elected vice chair of the RCGP, about resilience and the importance of it for GPs right now. In echoes of the HBR article, he identified three elements to GP resilience: pragmatic optimism; making do with what you have while making things better; and allowing yourself to think differently.

There are opportunities and new ways of working that can help general practice. Mike Holmes outlined some of these in our conversation. The hard bit for many GPs, as for anyone in a difficult situation, is letting go of the unfairness of what is happening and shifting into the “pragmatic optimism” that Mike describes.

Some GPs and practices have not yet been able to make this shift in mindset. Some will never make it. My life was probably changed forever (with a lot of help!) by shifting my focus from unhappiness with my rejection, to taking action to remedy it. I was accepted into Oxford at the second time of asking. Changing the direction of our lives starts with ourselves, with us releasing the emotional grip our current circumstances have on us, and changing our focus from causes and blame to our response and what we can do about it. This is being resilient.

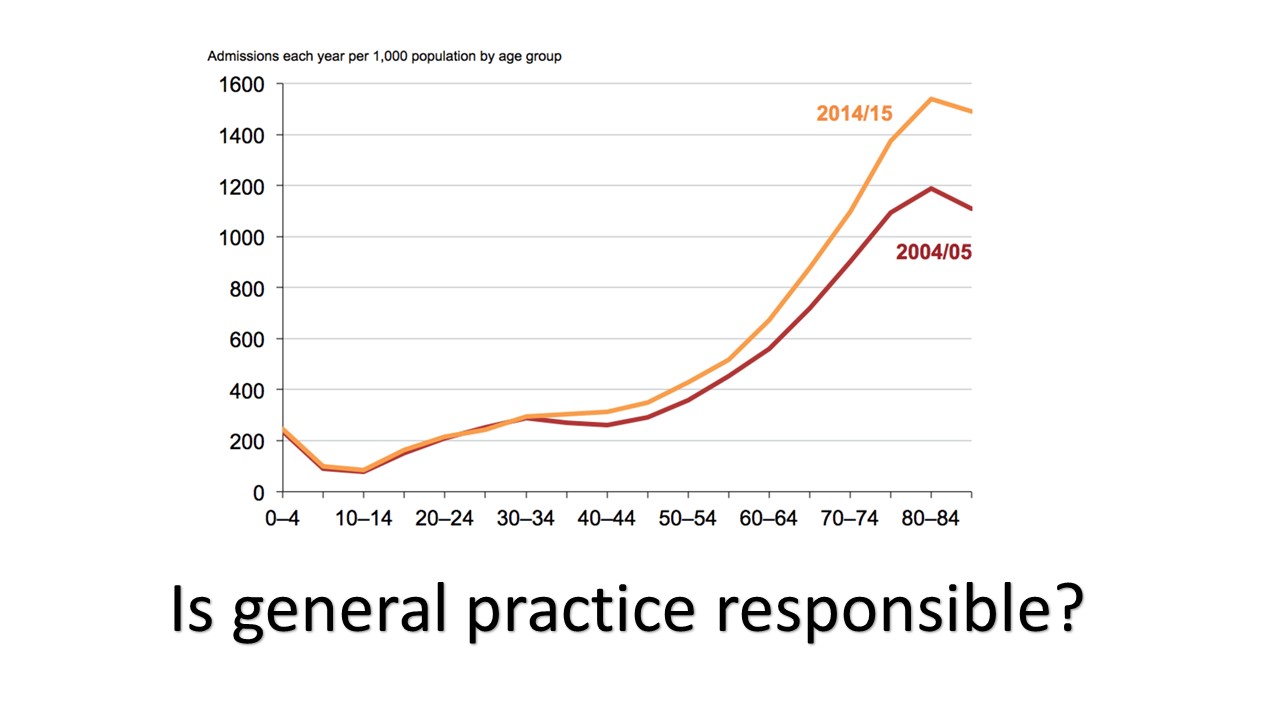
Is General Practice Responsible for the pressures in A&E?

Well what do you think? Is it? It may well depend who you are. If you are a GP you are unlikely to think so, but as a hospital Chief Executive, who has heard all about the workload and workforce pressures general practice is under, it is easy to draw the alternative conclusion.

But correlation, as my PhD wife constantly reminds me, is not the same as causation. The fact that general practice is struggling with workload pressure at the same time as there is rising demand in A&E only means the two are correlated. It doesn’t necessarily mean one causes the other. And so it is that research was published this week in the British Journal of General Practice looking at the factors affecting emergency department attendance. They found (drum roll),

“…the burden of multimorbidity is the strongest clinical predictor of ED attendance, which is independently associated with social deprivation. Low use of the GP surgery is associated with low attendance at ED. Unlike other studies, the authors found that adult patient experience of GP access, reported at practice level, did not predict use.”

In other words, people are living longer with more long term conditions. This in turn is causing the growth in demand, both for GP practices and A&E departments. The more GP consultations a person has, the more likely (for many groups) it is that they will also have more A&E attendances. Growing demand is the causative factor. Pressure on A&E departments and GP practices are simply correlated.

I am on Twitter (@BenXGowland – the X is actually my middle initial, as opposed to denoting membership of some secret society). You should be too. The GP I most enjoy following on Twitter is Dr Steve Kell (@SteveKellGP). He recently ran a survey (now I recognise I need to be careful here as having preached about the difference between correlation and causation, I know I am going to get stung on the validity of a small sample size, but nevertheless) which found that, of the 48(!) GP practices that responded, 81% had not been asked if they were busy or managing in the first week of the New Year, with only 19% saying that they had. Steve’s concern is that “sadly we value what we measure”.

But simply knowing that a problem exists (there is too much demand, and it is getting worse) does not actually help. Nor does finding someone to blame (whether it is GPs blaming hospitals, or vice versa, or the government, or Jeremy Hunt etc etc). The only real option is to work out what we can do about it (because even if there was more money, which there isn’t, there will never be enough).

Which brings me to another interesting exchange on Twitter involving my friend Dr Kell. His practice is a leading light in the Primary Care Home movement, and he announced on Twitter that his practice had achieved a (highly impressive) 5.5% year on year reduction in emergency admissions. Now that prompted a question in response from Professor Harris of Lakeside Health asking,

“where lies the incentive (other than patient benefit) of GPs working harder/differently/more productively if the £ benefits remain with trusts or CCGs?”

The essence of this question is what is the point of the primary care home, of groups of practices working with other agencies, and managing demand in a different way in the way that Dr Kell’s practice has, if there is no financial return for the practice? His response was that while there is no direct financial return, it makes things better for patients, for staff, and is more efficient.

If we think about this in the context of constantly rising demand, the challenge practices face is how to adapt to meet this demand in different ways. Not because there is a direct and immediate financial benefit, but because the current system is not working, and without change the system is likely to collapse. Everyone working in the system has a responsibility to understand and accept the current realities, and to think and act differently as a result, so that things can improve.

General practice is not responsible for the pressures A&E is experiencing, but it is responsible for adapting and finding new ways of dealing with the demand (like the work being undertaken within the primary care home sites) so that general practice, and the NHS, can continue to manage the rising burden of disease. And if you take nothing else away from this, at the very least you should follow @SteveKellGP on twitter…

Can independent contractors be trusted?

Over the festive period there has been something of a debate as to whether entities that are not NHS statutory bodies, but rather entities that contract with the NHS, can be trusted.  The debate has focussed on the evolving Accountable Care Organisations (ACOs).  For example, Dr Phil Hammond, a doctor, radio presenter and NHS commentator, said,

“I don’t think Accountable Care Organisations can be set up in the NHS without legislation stipulating their governance. They need to be statutory bodies to be properly accountable for the quality of care they deliver.” (via Twitter, Jan 1st)

Unfortunately, this brings the position of GP practices under the spotlight.  If this is true for ACOs, is it not also true for GP practices?

There is a fine line between being in the NHS and working with the NHS.  Back in 1948, amidst the protracted negotiations required to start the NHS, a deal was brokered whereby GPs would not become salaried employees, but rather remain independent, providing services via a national contract with the NHS.  This means GP practices provide NHS services, but are not NHS organisations, and “independent contractor” status was born.

Does the distinction between a statutory body and an independent contractor matter?  At first it mattered little, but times have changed since 1948.  In the 1980s the Conservative government privatised some of our national industries, including steel, railways, airports, gas, electricity, telecoms and water.  The NHS survived the cut, but instead the purchaser provider split was introduced in 1990.  Ever since, fears have remained that this was the first step in a plan to privatise the health service, and anything not a statutory NHS body is treated with suspicion.

Over 25 years later, we now approach the end game of the purchaser provider split, in a strange closing manoeuvre whereby the Health and Social Care Act of 2012 seemingly opened the NHS up to more competition, but in practice the NHS itself has closed competition down with a focus on integration through the Five Year Forward View.  Integrating organisations to work together within a fixed budget to improve the health of the local population has been termed “accountable care”.  Unfortunately, accountable care organisations are associated with the US, and fears have developed that they are the new Trojan horse to enable the privatisation of the NHS.

Enter the new importance of “independent contractor” status.  It is proposed that ACOs will contract with the NHS, rather than being statutory NHS bodies (just like GP practices).  This is a pragmatic response to not wanting new legislation (the only way to create new statutory bodies) or yet another top down reorganisation of the deck chairs, but instead wanting to enable and encourage local areas to develop local solutions that are right for them.  Unfortunately, that hasn’t stopped some campaigners from trying to take the Department of Health to court over their introduction.

I have written before about whether independent contractor status will form part of General Practice’s future.  My sense is the benefits (to GPs and to the delivery of health care) outweigh the costs and challenges.  The currency of the new world is trust.  People trust their GP, more than they trust their local NHS organisation, and much more than they trust national (statutory) NHS organisations.  Being a statutory part of the NHS won’t make the public trust GPs any more.

The same ultimately will be true of ACOs.  It is not what you are but what you do that matters, and their ability to build trust with the people they serve is likely to directly impact how successful they are.  Ironically, it is the relationships ACOs develop with their local (independent contractor) GPs that may determine how much their local population eventually choose to trust them.

General Practice Podcast – Highlights of the Year 2017

2017 was a brilliant year for the General Practice Podcast with 50 episodes and well over 2,000 downloads per month. In this graphic (below) we pick out a few of our favourite highlights including some of the most downloaded. We hope you enjoy. The Podcast returns on 8th January 2018 with a brand new episode and then continues with a new, free episode every week. You need never miss out on an episode – why not subscribe to our weekly newsletter here.

Open the graphic here: Podcast Highlights Graphic


Page 71 of 89
1697071727389

