I am astonished by how NHS England’s drive to remove patients from GP practice lists via the so-called “list cleansing” process has managed to go unchecked for so long. The practice is wrong, and yet it continues unabated.
I think the problem stems from an erroneous belief that there is merit to the process. In its focus on list cleansing in June 2026 the GPC leads with the phrase, “While GP England recognises the importance of ensuring that practice lists are accurate and up to date”, and then only goes on to only criticise the manner with which it is being done.
This need to agree with the principle of ensuring lists are accurate is a fundamental mistake and is hugely weakening general practice’s hand.
Reports of the total number of patients removed via this process vary between 300,000 and 830,000, but the fact is that there were 63.9M patients registered with GP practices in England in October 2025, and as of October 2026 there are 63.0M patients registered. This suggests the 830,000 figure is the closest of the two.
The impact of this removal is a loss to general practice as a whole of over £100M of core funding. This total is even greater, as there is an additional knock on impact on PCN DES and other funding streams that are based on population size.
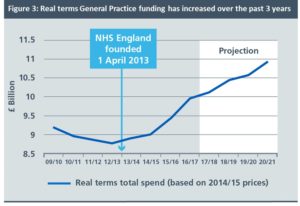
At the same time general practice is offering 20% more appointments now than in 2019, but funding in that period has barely kept up with inflation.
This is issue. This is why list cleansing is wrong. General practice is underfunded for the work it does. What list cleansing does is take the population-based nature of general practice funding and squeezes it so that practices receive even less funding, regardless of the amount of activity they are undertaking.
If GP practices should not be paid for patients who are not on their list, then they should be paid for all the work they are carrying out. But they are not. List cleansing abuses the population-based nature of GP funding by removing population-based payments without reimbursing the activity that this funding is currently subsidising.
For some practices list cleansing has meant a loss of 10% or more patients (and therefore income). Their costs meanwhile have not gone down at all. It is little wonder that these practices are feeling the pinch. The only surprise is that more of these practices have not had to close already.
Most practices are having to incur additional administration costs to validate the lists they are constantly being sent, and are having to prioritise this over patient facing tasks because of the financial impact on the core business.
Patients are suffering as well. The process seems to target patients who do not have English as a first language, those with learning difficulties, and those with insecure housing. It is not right.
It is not good enough to say that the money taken out of general practice by this crude tool will be reinvested in general practice (as NHS England purportedly have). For one there is no guarantee at this point that this will actually happen, and it already seems highly unlikely that the 2026/27 money will come back to general practice. For two how do we know that any reinvestment will do more good than the harm caused by this mechanism of disinvestment? And for three there should, as an absolute minimum, be a transition plan to support those practices most affected (which there is not).
List cleansing is wrong. It should not be happening. It is high time general practice, and those organisations representing it, took a much stronger stance in kicking back against this blunt and damaging practice.