Primary Care Networks: Who sets the agenda?

It has been a challenging start for Primary Care Networks (PCNs). From first settling the membership and getting the network agreement signed, to then immediately having to tackle any half day closure issues and practices who were not providing extended hours, it is fair to say the journey so far has not been easy. But where does the focus now lie for PCNs?

The risk for PCNs is that they continue to be recipients of an agenda and a timetable set by others. Now PCNs are in place, there are a plethora of organisations and individuals keen to meet them and talk about their work and their programme and how the PCN can support it. The number of meeting requests for the new PCN CDs is growing, and will doubtless accelerate once the holidays are over and September arrives.

PCNs are different from CCGs and other NHS organisations, in that they are not statutory bodies. The NHS hierarchy has no formal control over them. Born out of the GP contract, they are contractual constructs and as such are independent contractors in the same way that GP practices are. If it is not in the contract, the PCN can choose not to do it.

There is a power in this position. Clearly it is going to be in the interest of the PCN to build constructive relationships with other organisations (even if the primary motivation is to make delivering the future contractual requirements easier!), and to take actions to support the local population. But this is different to letting others set the agenda for your PCN, in terms of what it is trying to do and what it spends its time discussing and working on.

The establishment of a PCN is an exercise in change management for general practice. Changes succeed or fail depending on the extent to which the problem the change is trying to solve is clear, the extent to which those involved in the change are bought in to solving the identified problem together, and the ability to show progress over time towards solving the problem (I would strongly recommend you take half an hour to read this book if you haven’t already).

This means to be successful PCNs need to exist not because the contract mandates that they do, but as an enabler to solving the problem(s) the practices have identified. It is critical PCN practices spend time agreeing exactly how they want to maximise the benefit of the new PCN, whether that is the outcomes for the local population, the financial sustainability of the member practices, the workload of the member GP partners, or whatever the key local challenges are.

Once this is clear, setting the agenda is much more straightforward. The PCN will prioritise anything that supports delivery of its aim, and de-prioritise anything that does not. Control of the agenda comes from the PCN itself, not from outside. If progress is monitored by the use of some agreed regular measurements, this focus will remain in place as the months progress.

But without a clear purpose, PCNs run the risk that their agenda will be set by others, that they will achieve very little that makes a difference locally, and that any initial enthusiasm and support from practices will quickly wane. As the contractual requirements lessen for the remainder of the year, and as PCN development monies emerge, if you have not done so already now is the time for member practices to establish and agree what they want the PCN to achieve, and then to make sure it controls the agenda and how its precious time is used to ensuring that goal is delivered.


 

Should PCNs have a national voice?

There was an interesting recent debate on one of the national WhatsApp groups about whether there is a role for an independent national PCN voice. Opinion was divided, with strong proponents both for and against.

The argument for goes along the lines that PCNs are something new (with a new cadre of PCN Clinical Directors) doing something different and more inclusive than general practice, and hence need to be represented at a national level in a different way to the GPC/how core general practice is represented.

I think there are two main reasons why this is not a good idea. First, it will weaken the national voice of general practice. General practice remains in crisis, despite the new contract and the formation of PCNs. It is critical that general practice retains a strong national voice. It currently has this through the GPC. If a separate voice for PCNs develops, it risks enabling the government, NHS England and national bodies to bypass the GPC, and push initiatives and new ways of working onto general practice via the PCN route. The greater dependence general practice has on PCN funding, the greater this risk becomes.

Second, it could limit local PCN flexibility. There are people working hard to try and enable the development of PCNs to be determined at a local level. One of the key strengths of PCNs is as local network enablers, bringing general practice together with a wide range of local stakeholders for the betterment of local outcomes. Each place is different, and will need different strategies and ways of working, and (more importantly) will want to control how this happens for itself. The old mentality of being dictated to from on-high needs to be replaced with a vibrant local determinism, a shift far less likely to happen if a national PCN representative body exists.

PCNs do, however, need a strong voice within their local integrated care system (ICS). Part of the PCN Clinical Director role is to represent the PCN within the local ICS, and how effectively this happens may determine whether there is any overall shift of resources (and workload) from secondary to primary care, and whether the system invests in primary care.

The key to this voice being strong is for general practice to ensure it presents a united front locally. If general practice is represented by a federation, the LMC and PCNs, none of whom can agree on what they want or how they want it, the voice is divided and the overall voice is diluted. Ultimately this internal division will end up in less resource being shifted to primary care.

The desire for a separate PCN voice comes from a sense of some GPs and practices not feeling represented. The solution, however, is not to create a separate voice for them, but to work hard to establish an inclusive, strong, unified voice for general practice, and to work to overcome the often historic barriers and disputes that exist within general practice for the benefit of all.

Here at Ockham Healthcare we have produced a free guide for PCNs which outlines 10 practical steps for PCNs to establish a powerful voice. It is free for subscribers – to subscribe simply click here. A unified PCN voice at a system level, and a single general practice voice at a national level, will maximise the overall impact of general practice on the system, and increase its chances of emerging from its current challenges.

The danger of the PCN “maturity matrix”

How will you know if your PCN is “mature”? What is maturity of a PCN, and who is to decide when you have reached it?

There is a danger that NHS management speak (I think it is fair to categorise “PCN maturity matrix” in this way!) can generate a life of its own. The PCN guidance suggests a national PCN maturity matrix will be produced (which was due at the end of July, and so should appear any day now). The PCN frequently asked questions says that “all systems should use the provided maturity matrix in the first instance to assist with assessing the relative maturity of networks”.

This response inevitably gave rise to the next question, “Will the PCN maturity matrix be used for performance management?”, and we are assured that, “the maturity matrix is not an assurance vehicle for PCN performance”. However, it does seem that creating a PCN development plan based on an assessment against this matrix will be a required gateway for accessing PCN development monies.

While there is clearly a value in laying out for nascent PCNs what “good” looks like, the danger of a national PCN maturity matrix is that it could impose requirements or expectations upon a PCN beyond those set in the national contract. It could start to impinge not just on what PCNs have to do, but how they have to do it. There is a fine line between a national framework (and NHS England has pushed back on any attempts by local areas to create their own framework) that helps PCNs to develop, and one the determines how they should operate.

Rather than let a national team decide what maturity looks like for your PCN, it may be better for the PCN itself to determine what maturity looks like. A PCN that decides for itself where it is going and how it will develop will be likely to progress more quickly, as it will retain ownership of its future. Equally, if a national framework is used to shift autonomy away from member practices and assert top down control on how PCNs are to operate, progress is likely to be laboured.

So what is maturity for your PCN? I would argue it is essentially framed around the ability to deliver:

  • The ability of the PCN to deliver across the member practices (see last week’s blog for the importance of the relationships between the practices, an area unlikely to be given prominence in the national maturity matrix)
  • The ability of the PCN to support member practices who struggle with delivery, and to support the delivery of core general practice
  • The ability to remove blocks to delivery as they occur, such as resolving disputes between member practices
  • The ability of the PCN to build productive relationships with system partners to enable effective delivery
  • Having the infrastructure in place to enable effective delivery, such as data sharing, access to information, ability to attract, employ and retain staff, project management etc.
  • The ability to access good ideas, new ways of working, solutions to challenges and support when needed from both inside and outside of the PCN to enable delivery
  • Having effective leadership in place that can make delivery happen

Your PCN will inevitably have its own view on what its maturity looks like. The key is a good PCN is not necessarily one that is assessed as “mature” against all elements of a nationally set maturity matrix, but one that can turn ideas into actions and into tangible results, and is able to make the biggest possible difference for its practices and its patients.

Clearly it is worth jumping through a few hoops to access what is a significant amount of PCN development money. But don’t let the process determine how you will develop. Make that decision for yourselves.

The relationship between a practice and a PCN

As a GP practice, how do you think of your PCN?  Do you see it as a joint initiative between you and your fellow practices to work together to make life better for each other and for your patients? Or do you see it as something you have to do because the GP contract/CCG/government have decreed it?

When you think of the work that does and will take place through the PCN, do you see it as practice work done jointly with the other PCN practices? Or is it “PCN work”, separate from the work you do in the practice?

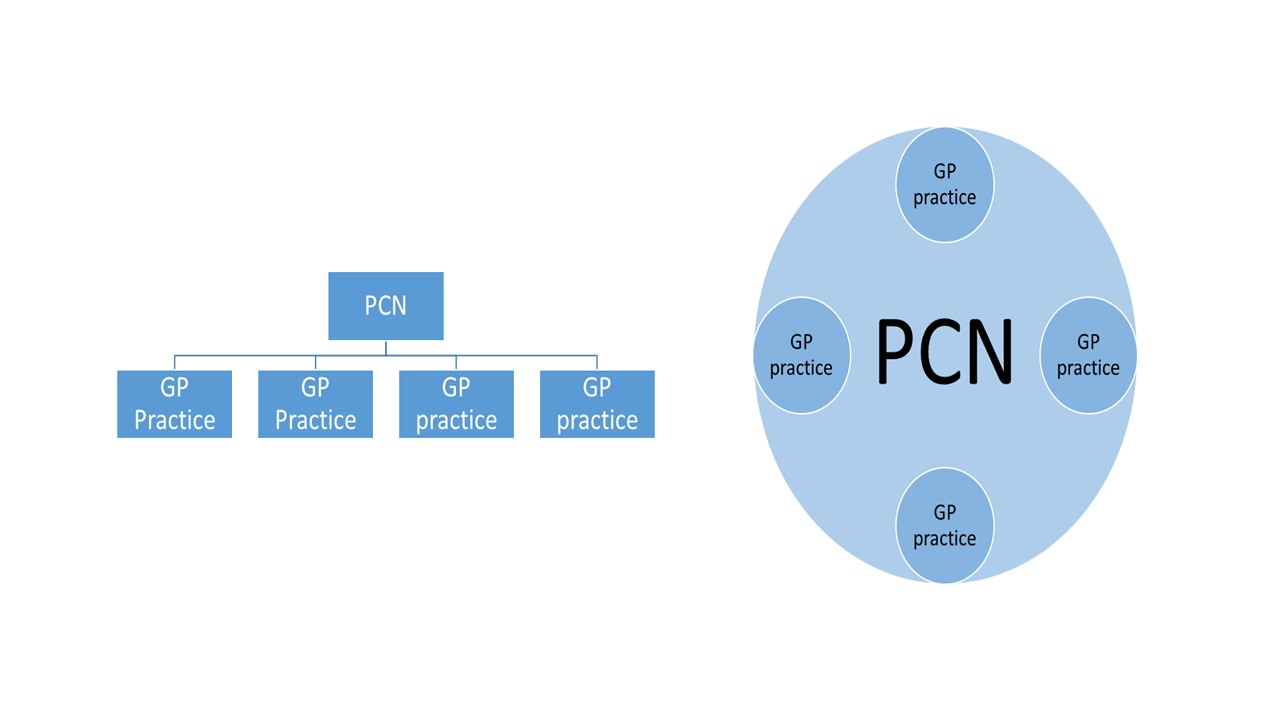
How the relationship with the PCN “feels” to the member practices is crucial.  If it feels like the PCN sits above the practices, in a hierarchical fashion (as depicted on the left below), there is going to be a perceived separation between the practices and the PCN.  The work of the PCN will feel separate from the “core” work of practices, and the PCN will run the risk of being a burden to practices both in terms of workload and finances.

If the PCN feels like it is the group of practices working together (as depicted on the right), then the opportunity of PCNs for practices is greater.  The work of the PCN will support and become part of the core work of practices, rather than operate separately from it.  The PCN work becomes the way the practices can improve their workload and their finances.

Even within one PCN the attitude towards it by member practices can vary.  You may have one practice viewing it as something separate, but another seeing it as integral to the practice and how it operates.  This point was brought home to me this week in a conversation I had with Paul Deffley from Practice Unbound (watch out for this episode of the General Practice podcast coming up in August).  He described a pharmacist operating across two practices.  It was the same pharmacist following exactly the same processes and seeing exactly the same types of patient.

The reaction to the pharmacist by the two practices was completely different.  One practice quickly got to the place where they couldn’t imagine how they ever managed without a pharmacist before, and thought the impact on the GPs and on the practice had been enormous.  The other practice was far less enamoured, and if anything thought the pharmacist had created additional work for the GPs.  The main difference was the first practice had actively engaged with the pharmacist, invited them to team meetings, and made them part of the practice “family”, whereas the other practice had never embraced the pharmacist in the same way.

If a practice welcomes and takes on the PCN initiatives as part of the way they are now working, the impact for the individual practice, and the for the PCN overall is likely to be considerable.  If a practice keeps its focus on what it can control, and keeps the PCN work at arm’s length, the impact will be far less.

The implications of this are huge.  It impacts the extent PCNs are able to make changes to meet the needs of practices, and how effectively PCNs can support the sustainability of general practice.  It will directly affect the finances.  Practices would willingly pay a third of the funding for new services that they want, if the “centre” is chipping in 70%.  Subsidising an arms-length PCN initiative for the same amount is an entirely different matter.

It is not the existence of PCNs that is important, but how they operate.  This will vary considerably across the country.  For all the talk about PCN plans, maturity matrices, and development programmes, my number one focus right now for making a PCN successful would be on getting the relationship between the practices and the PCN right.

The Top Ten Most Popular General Practice Podcasts of All Time!

While the General Practice podcast is having a few week’s holiday (it will be back on the 29th July), it is a good time to catch up on some of the episodes you may have missed.  The podcast started in 2016, and there are now over 170 episodes, so choosing the best ones might be a challenge!  To help you I’ve identified the 10 most downloaded episodes, as they may be a good place to start. Here, in traditional reverse order, are…

  1. Marie-Anne Essam – Social Prescribing and Link Workers

In this episode, I spoke to Marie-Anne Essam a GP in Herts Valley and an enthusiastic ambassador for social prescribing. She explained what it is and told a powerful story about a patient of hers which amply illustrated the value of social prescription. She also talked about the specific role of link workers including their salary, their competences and their likely backgrounds.

  1. Riaz Jetha – The new Primary Care Network DES

In the days immediately following the publication of the new network DES special guest Dr Riaz Jetha and I discussed the newly released specification. We looked at the nature of the network agreement, the role of federations, how clinical leaders were to be recruited, population size, funding and much more.

  1. Neha Shah and Colin Haw – The practical implications of establishing PCNs

In this episode I was joined by Neha Shah, a Legal Director from Capsticks and Accountant Colin Haw from BHP Chartered Accountants.  They discussed some of the legal, financial and governance issues facing general practice as it began to establish Primary Care Networks. Specifically they considered how networks would be hosted and the implications for liability, choices around the organisational form, employment contracts, pensions and VAT.

  1. Ben Gowland – The new GP contract

In this episode the tables were turned with me in the hot seat detailing the importance of the new GP contract. I explained, in the week after the publication of the new GP contract, why it is a huge opportunity and gave me optimism for the future. I described the way that the additional £2.8bn attached to the contract was expected to flow, how primary care networks were to be developed and how they would be staffed. I also gave some practical advice to practices about what they should be doing then, in preparation for the year ahead.

  1. Ceinwen Mannall – Education for clinical pharmacists in general practice

In this episode I spoke to Ceinwen Mannall, who is the national lead for Clinical Pharmacists in General Practice education at the Centre for Postgraduate Pharmacy Education (CPPE).  She told me about the training available to pharmacists moving into general practice, the impact and value that pharmacists have and tips for practices thinking of employing a clinical pharmacist.

  1. Tom Howseman – Better managing demand through pre-triage protocols

Tom Howseman is a GP Partner in a large urban practice in Northampton. When their complement of GP partners fell from twelve to six due to retirements and they couldn’t recruit they decided to adopt a more multi-disciplinary approach. Over the last two years they have introduced and refined a system of pre-triage protocols which enable reception staff to collect information from patients presenting on the day which is then helpful to the pre-triage clinicians in directing those patients to the appropriate member of the emergency care team. 20,000 additional appointments have been created through this system and in this episode Tom explained how they have done it.

  1. Rachel Morris – GP stress, burnout and resilience

Rachel Morris is a GP, an executive coach and presenter with Red Whale; producers of the famous GP Update. In this episode she looked at GP resilience; what it is and how can you acquire it. She considered the causes of stress and burnout and pointed to a range of useful resources GPs can use to develop their personal resilience.

  1. Nikki Kanani – The new GP Contract – Part 1

My special guest for two weeks in February/March this year was Dr Nikki Kanani, one of the chief architects of the new GP contract. Nikki is a GP in south-east London and is currently Director of Primary Care for NHS England. This is the first of two discussions with Nikki in the Top Ten and in this part, she explained the role of primary care networks in general practice and looked in detail at the funding behind the new contract. She explained how the money would be delivered and for what it would be made available including 20,000 new staff, support for clinical leadership and Investment in innovation.

  1. Nikki Kanani – The new GP Contract – Part 2

In this second part of the interview with Dr Nikki Kanani she addressed the concerns of podcast listeners about primary care networks including population size, hosting of the networks and the role of federations. She looked at how clinical leaders should be identified and focused in detail on the timetable from March 2019 onwards and what practices should be doing at that time to guarantee success.

  1. Rachel Morris – Developing GP leaders

Top of the pile, and more popular than even Nikki Kanani, sees the second entry for Dr Rachel Morris.  In this podcast Rachel described two courses that Red Whale were running aimed at developing leadership skills in primary care leaders. The first is Lead. Manage. Thrive! – a very popular one day course in management skills for GPs. The second wass a new course on Working At Scale. Rachel explained how and why the programmes were developed, who the training is aimed at and what the courses cover.

So that’s the current Top Ten. Don’t forget, if you’d like to see something featured in a future episode of the General Practice Podcast or you’ve got a story to tell yourself, just email me at ben@ockham.healthcare or DM me on Twitter @benxgowland and we’ll do the rest.

Page 56 of 89
1545556575889