The Top Ten Most Popular General Practice Podcasts of All Time!

While the General Practice podcast is having a few week’s holiday (it will be back on the 29th July), it is a good time to catch up on some of the episodes you may have missed.  The podcast started in 2016, and there are now over 170 episodes, so choosing the best ones might be a challenge!  To help you I’ve identified the 10 most downloaded episodes, as they may be a good place to start. Here, in traditional reverse order, are…

  1. Marie-Anne Essam – Social Prescribing and Link Workers

In this episode, I spoke to Marie-Anne Essam a GP in Herts Valley and an enthusiastic ambassador for social prescribing. She explained what it is and told a powerful story about a patient of hers which amply illustrated the value of social prescription. She also talked about the specific role of link workers including their salary, their competences and their likely backgrounds.

  1. Riaz Jetha – The new Primary Care Network DES

In the days immediately following the publication of the new network DES special guest Dr Riaz Jetha and I discussed the newly released specification. We looked at the nature of the network agreement, the role of federations, how clinical leaders were to be recruited, population size, funding and much more.

  1. Neha Shah and Colin Haw – The practical implications of establishing PCNs

In this episode I was joined by Neha Shah, a Legal Director from Capsticks and Accountant Colin Haw from BHP Chartered Accountants.  They discussed some of the legal, financial and governance issues facing general practice as it began to establish Primary Care Networks. Specifically they considered how networks would be hosted and the implications for liability, choices around the organisational form, employment contracts, pensions and VAT.

  1. Ben Gowland – The new GP contract

In this episode the tables were turned with me in the hot seat detailing the importance of the new GP contract. I explained, in the week after the publication of the new GP contract, why it is a huge opportunity and gave me optimism for the future. I described the way that the additional £2.8bn attached to the contract was expected to flow, how primary care networks were to be developed and how they would be staffed. I also gave some practical advice to practices about what they should be doing then, in preparation for the year ahead.

  1. Ceinwen Mannall – Education for clinical pharmacists in general practice

In this episode I spoke to Ceinwen Mannall, who is the national lead for Clinical Pharmacists in General Practice education at the Centre for Postgraduate Pharmacy Education (CPPE).  She told me about the training available to pharmacists moving into general practice, the impact and value that pharmacists have and tips for practices thinking of employing a clinical pharmacist.

  1. Tom Howseman – Better managing demand through pre-triage protocols

Tom Howseman is a GP Partner in a large urban practice in Northampton. When their complement of GP partners fell from twelve to six due to retirements and they couldn’t recruit they decided to adopt a more multi-disciplinary approach. Over the last two years they have introduced and refined a system of pre-triage protocols which enable reception staff to collect information from patients presenting on the day which is then helpful to the pre-triage clinicians in directing those patients to the appropriate member of the emergency care team. 20,000 additional appointments have been created through this system and in this episode Tom explained how they have done it.

  1. Rachel Morris – GP stress, burnout and resilience

Rachel Morris is a GP, an executive coach and presenter with Red Whale; producers of the famous GP Update. In this episode she looked at GP resilience; what it is and how can you acquire it. She considered the causes of stress and burnout and pointed to a range of useful resources GPs can use to develop their personal resilience.

  1. Nikki Kanani – The new GP Contract – Part 1

My special guest for two weeks in February/March this year was Dr Nikki Kanani, one of the chief architects of the new GP contract. Nikki is a GP in south-east London and is currently Director of Primary Care for NHS England. This is the first of two discussions with Nikki in the Top Ten and in this part, she explained the role of primary care networks in general practice and looked in detail at the funding behind the new contract. She explained how the money would be delivered and for what it would be made available including 20,000 new staff, support for clinical leadership and Investment in innovation.

  1. Nikki Kanani – The new GP Contract – Part 2

In this second part of the interview with Dr Nikki Kanani she addressed the concerns of podcast listeners about primary care networks including population size, hosting of the networks and the role of federations. She looked at how clinical leaders should be identified and focused in detail on the timetable from March 2019 onwards and what practices should be doing at that time to guarantee success.

  1. Rachel Morris – Developing GP leaders

Top of the pile, and more popular than even Nikki Kanani, sees the second entry for Dr Rachel Morris.  In this podcast Rachel described two courses that Red Whale were running aimed at developing leadership skills in primary care leaders. The first is Lead. Manage. Thrive! – a very popular one day course in management skills for GPs. The second wass a new course on Working At Scale. Rachel explained how and why the programmes were developed, who the training is aimed at and what the courses cover.

So that’s the current Top Ten. Don’t forget, if you’d like to see something featured in a future episode of the General Practice Podcast or you’ve got a story to tell yourself, just email me at ben@ockham.healthcare or DM me on Twitter @benxgowland and we’ll do the rest.

Guest Blog – Nick Sharples – PCNs and Social Prescribers

With the vast majority of Practices now a part of a Primary Care Network, and a week into the formal ‘Go Live’ date for PCNs to start operating, PCN Clinical Directors and their teams are starting to consider recruiting the Social Prescribers for whom the NHS are providing full funding in the current financial year. Now is perhaps therefore an opportune time to review the ways in which PCNs can best recruit, train and introduce Social Prescribing to their new organisations.

Our engagement with PCNs regarding training for Social Prescribers has identified a number of different models currently being considered by PCNs. Perhaps the most innovative approach is to realise that the opportunity is significantly greater than simply recruiting an additional member of staff. These PCNs are already examining ways in which the recruitment of the new Social Prescriber can herald the introduction of a Social Prescribing culture and the provision of a comprehensive Social Prescribing Service throughout the PCN. This can be achieved by leveraging the people skills of the health professionals already working within PCN Practices and recruiting suitable volunteers from the patient community to support the Social Prescriber, who sits at the heart of the new Social Prescribing Service.

Introducing a Sustainable and Comprehensive Social Prescribing Service across the PCN

It may seem a little counter intuitive, if not naïve, to believe that one can create a sustainable and comprehensive SP service with just a single Link Worker to support potentially 50,000 patients. But with imagination and determination it is not impossible. The key is in being prepared to engage and upskill existing staff and leverage them to support the primary Social Prescriber, and in doing so to help the new funded Social Prescriber be as effective in their role as possible.

Practice Social Prescribing Champions

With the average PCN in England likely to comprise between 3 – 6 Practices (based on an average list size of 8,490 in Dec 2018), forward thinking PCNs are seeking to train up not just the primary Social prescriber but a suitable volunteer member of staff with the right people skills from each of the PCN practices. These Social Prescribing Champions in each Practice will facilitate and smooth the referral process to the primary Social Prescriber, actively recruit volunteers from their patient communities to assist the Social Prescribing Service and will be trained and able to stand in for the primary Social Prescriber when he or she is on holiday or off sick.

Where appointment capacity becomes a problem for the primary Social Prescriber, as experience with the introduction of other allied health professionals suggests it will do, these Practice Champions, trained to the same level as the primary Social Prescriber, can undertake their own Social Prescribing, working in their own Practice and with their own patients to alleviate waiting times for the primary Social Prescriber. This may not be practical in every Practice and will depend on the clinical priorities determined by the GPs, but some are starting with a half day a week of Prescribing from their own trained Champion and building up as appropriate. However, if started, this needs to become a long-term commitment with a long notice period, as continuity of Link Worker is fundamental to building the trust and relationship with the patient.

Volunteers

There is much emerging evidence that using volunteers alongside trained Social Prescribers can significantly enhance the scope and reach of a scheme. Volunteers can provide emotional and practical support to service users and have in some cases been further trained as link workers to provide facilitated referrals to some of the community groups within the local area. They come from a wide range of backgrounds; some may be recruited from patients who have been referred to the service and wish to volunteer as part of their social prescription; others may come from the Patient Participation Group and yet more may be locally recruited volunteers with multiple skills and experience of life who wish to offer something back to the community. Recruitment of a cadre of volunteers at PCN Practices will significantly increase the overall effectiveness of the Social Prescribing service.
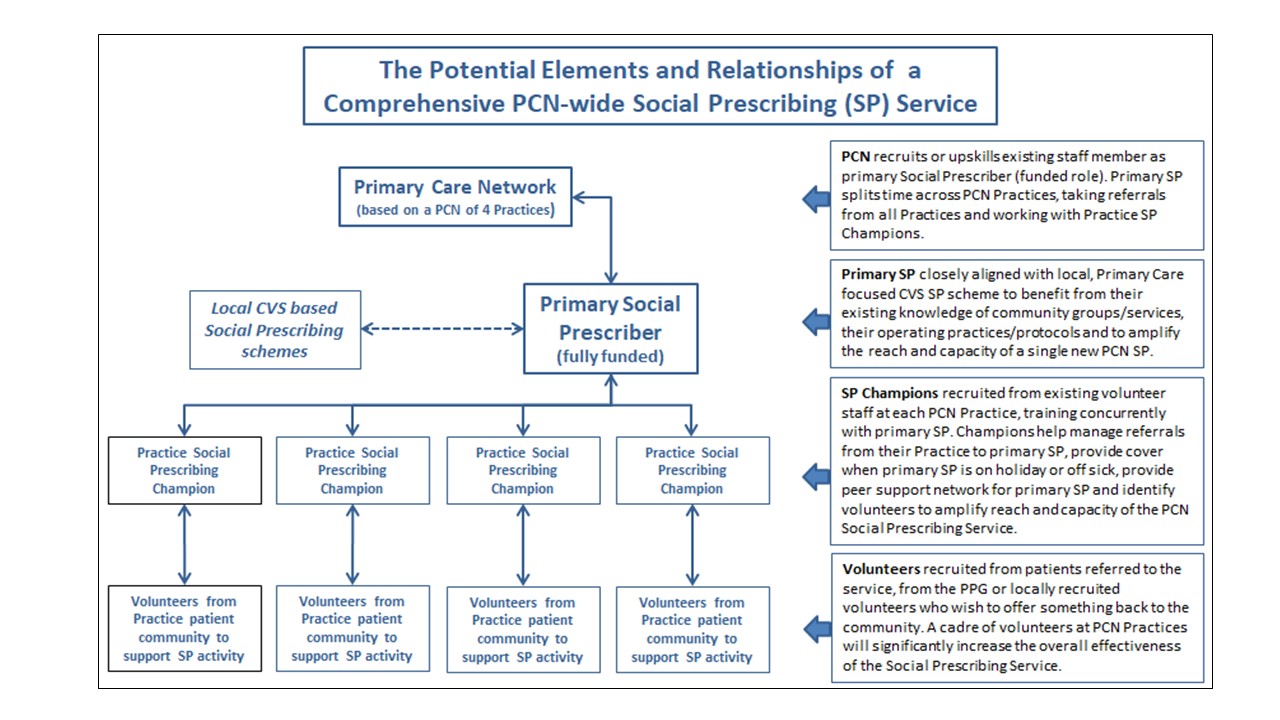
A Potential Structure Suitable for a PCN to Establish a Comprehensive Social Prescribing Service (Click image to enlarge)


The Primary Social Prescriber – PCN Controlled or Aligned with Existing Local Scheme?

Given the challenges of expecting a single, unsupported Link Worker to make a significant difference in a patient community of up to 50,000, NHS(E) and the Social Prescribing Network have both suggested that the most effective way of managing new PCN Link Workers is to closely align them to an existing Social Prescribing Scheme in the area. This can range from close collaboration and sharing of administration, resources and operating protocols where appropriate, through to fully outsourcing the employment and management of the Social Prescriber to a local CVS scheme.

For both outsourcing the role and for close collaboration, the choice of host CVS based scheme is crucial. Ideally it should be already working with and taking referrals from Primary Care in some respect so that the working practices and administrative processes are similar. For example, whilst a local Social Housing based Social Prescribing scheme might be delivering great results, it is unlikely to be working closely with GP Practices in the manner that will be expected of a PCN based Social Prescriber. The desired synergies from aligning the PCN Social Prescriber with such a scheme are therefore unlikely to be realised.

Recruiting the Social Prescriber – Upskill or Recruit from Outside?

PCNs are currently considering whether to upskill an existing member of staff as a Social Prescriber or recruit from outside. Recruiting skilled and experienced Social Prescribers from existing schemes in the voluntary sector is a possibility, but this does nothing to expand overall Social Prescribing capacity and is likely to lead to ill feeling between Primary Care and existing Social Prescribing schemes. Additionally, in large urban areas with many PCNs seeking to recruit Social Prescribers, the availability of external, currently unemployed candidates is likely to be quickly exhausted.

Up skilling of existing Practice staff has many benefits; they are already known to GPs within the Practice/PCN, they will be familiar with procedures in the Practice and, if their PCN has undertaken Active Signposting training for their Reception teams, they will have a good understanding of the available services and community groups operating in the area. In short, after suitable training in the specific skills needed by a Social Prescriber, they are more likely to be ready to hit the ground running.

The only real prerequisite for upskilling an existing member of staff is that they fulfil the person specification of a Social Prescriber. These soft people skills are inherent in those who make the best Social Prescribers, and it is no surprise that many come to Social Prescribing from the caring professions. These soft people skills include a natural desire to help people and give them time, the ability to listen, empathy, patience, excellent communication and organisation skills, the ability to inspire trust and confidence, and the flexibility, resilience and initiative to work on their own with minimal direction. Nurses, HCAs, some Receptionists, Social workers and voluntary workers often make good Link Workers.

Training the New Social Prescriber and Practice Champions

If recruited directly from a local CVS based scheme working closely with Primary Care, the new Social Prescriber is unlikely to need much additional training. In all other circumstances however, the newly recruited Prescriber will require upskilling in the specific skills used by Social Prescribers. These include Active Listening, Motivational Interviewing, Health Coaching, preparing Care Plans and managing the administrative processes required of the role so that they align with those of the PCN.

Motivational Interviewing skills are particularly important in a Primary Care setting, where the percentage of referred patients who are at the pre-contemplation stage of the change cycle tends to be higher than for service users in CVS based schemes.

If adopting the PCN Social Prescribing service structure suggested above, the training will also need to encompass the Practice Social Prescribing Champions who, by definition, are unlikely to possess any existing Social Prescribing skills. Training the new primary Social Prescriber alongside the volunteer Practice Champions is a wholly positive approach and should be considered the default.    It establishes the supportive network and close personal and professional relationships needed for the Social Prescribing service to operate effectively across the PCN.

If looking for external training support, PCNs would be advised to retain a training organisation, such as DNA Insight, who will train the PCN’s Social Prescribers as a single group and who will customise the training to suit the specific needs and operating protocols of the PCN. Facilitated Active Learning Sets, such as those included in DNA Insight’s SocialPrescriberPlus™ programme, help the whole Social Prescribing team to build an enduring and close personal and professional network that can address challenges, identify and build on Best Practice, increase resilience within the team and meet the priorities set by the PCN Clinical Director and the Practices.

 Conclusion

In conclusion, the additional resource of a fully funded Social Prescriber to work across the PCN is a wholly positive development. On their own however, the challenge of supporting up to 50,000 patients is likely to be overwhelming and the expected benefits may not extend as deeply into the PCN Practices as had been hoped, especially once the Social Prescriber’s list has filled up and waiting times start to become unacceptable.

PCNs can however take an innovative approach to creating a sustainable and effective PCN-wide Social Prescribing Service – by training, utilising and empowering volunteer Practice Social Prescribing Champions to support the primary Social Prescriber. These Champions in turn recruit volunteers from the local/patient community with lived experience, some of whom may have benefited from the service, to provide practical assistance and support to the team, allowing the team to focus on delivering the best possible care to the greatest possible number of patients.

Other Social Prescribing models are of course available and are equally valid. The key outtake is that with initiative, ambition and innovation it is entirely possible to create a comprehensive Social Prescribing Service for a Primary Care Network, despite only having funding for a single Social Prescriber.

Useful Resources and Social Prescribing networks for PCNs and Link Workers

  • Twitter Social Prescribing Wednesday – @SocialPresHour – every other Wednesday and hosted/organised by Elemental
  • National Association of Link Workers www.connectlink.org Christiana Melam christiana@connectlink.org Professional body representing Social Prescribers/Link Workers with lots of useful resources for Link Workers and those employing them.****************

Nick Sharples is a Director of DNA Insight Ltd, a GP training consultancy specialising in providing advice and training in the High Impact Actions of the GP Forward View. The SocialPrescriberPlus™ programme is designed for new or existing Social Prescribers and Link Workers, whether GP-based or working in the community. For more information please call us on 0800 978 8323 or visit our website at dnainsight.co.uk


 

What’s next for PCNs: The first 100 days…

You made it! The 1st July has come and gone. The Primary Care Network is in place, the network agreement (largely) agreed and signed, you have a way forward on extended hours, and now you are “live”. But what is next for the PCN Clinical Director? Now you are officially on the payroll, it is time for the first 100 days.

Senior leaders often start new roles with a plan for their first 100 days. They are important because they set the tone for how things will be under your leadership. Here are seven things for new PCN Clinical Directors to consider making part of your 100-day plan.

1 Focus on relationships over delivery

The biggest mistake eager new leaders make is to have an almost zealous focus on delivering sweeping changes as early as possible in their tenure. They feel the need to prove themselves in the job by showing they can make change happen fast.

Practices are already nervous about the introduction of PCNs. A new PCN CD dictating to practices how things are going to be within a few weeks of taking on the role is going to make these feelings worse. Even if you are able to bulldoze through how the pharmacist is going to work in every practice, it will be at the cost of the trust, discretionary effort, and support that you will need going forward.

Instead, focus on listening to practices, understanding their different needs and challenges, and the concerns and hopes they have about PCNs. At the same time, identify the key leaders in the community, mental health and voluntary organisations in your area. Ask to meet them, don’t wait for them to approach you. A network of strong relationships will be essential for future success.

2 Ensure a communication system is in place

Communication across all members of a practice is not always great.   If practices don’t know what the PCN is up to, mistrust will grow. The challenge for PCNs is enabling two-way communication across a group of practices. Ask practices what they want – a WhatsApp group, a weekly email, or whatever will work locally, and how often, and put it in place. If you achieve nothing other than putting an effective communication system in place you can consider your first 100 days a success!

3 Agree what success for the PCN looks like

You may be one of the few PCNs who before they got lost in the details of network agreements and extended hours took time to agree what the PCN was for, what its purpose was, and how success would be measured. But if not, now is the time for the PCN CD to find out from practices what success for the PCN means to them, and then to play back something that all can relate to, so both you and the practices are clear on what exactly it is you are trying to do in your role as PCN CD.

4 Under-promise and over-deliver

This sounds simple, but all too often new leaders make grand promises early on to try and build support based on what they are going to do. They then spend the rest of their time having to explain why they haven’t lived up to their initial claims. It is far better to be cautious in what you say you can deliver, and to build trust as you go by not only consistently doing what you said you would do, but often times achieving considerably more.

5 Select the Meetings you attend carefully

The NHS has a nasty habit of taking new leaders and swamping them with more meetings than it is possible for any diary to bear. The challenge in your first 100 days is to keep as much control of your time as you can. You must decide the meetings you go to; do not let the system decide for you. Ultimately you will be judged on the success of your network, not on the number of meetings you have attended. If you are always in meetings you will have very little time for real delivery, and very little time for the visible presence you will need at practice level to build that all-important support and trust.

6 Find your personal support

Leadership is lonely. You will, however supportive practices are right now, have to make some very tough and most likely unpopular decisions. There will be times when choosing the right way forward will be hard, and you won’t know what to do. These are the times when you will need support; people you can turn to who you can trust and who will help you work things through. Better to find this support and have it in place before you need it, rather than wait until the inevitable crisis arises. It may be a trusted colleague in your PCN, the CD of a neighbouring PCN (you are all on the same side), or someone else whose experience and opinion you value. Make finding this support a priority for your first 100 days.

7 Deliver some small wins

Now remember you are not trying to deliver any sweeping changes in your first 100 days. By small win we are not talking about anything major. But if from your conversations with practices, listening to GPs, and meeting local stakeholders there are things you see that can be done that are relatively easy to implement (without generating antibodies!) then make them happen. No one is expecting a miracle straight away, and setting a tone of positive change can create momentum for the bigger challenges ahead.

Pack or pride – how should PCNs operate?

“The strength of the pack is the wolf, and the strength of the wolf is the pack.” Rudyard Kipling

There is a nervousness amongst GP practices in the intertwining of their fates with those of other practices through PCNs.  The move to robust PCN network agreements can be about protecting the higher performing practices from being ‘dragged’ down by those who are not doing so well.

Equally, as GP practices choose the PCN they are to be part of, there is a tendency for competitiveness between PCNs to emerge.  Instinctively many GPs and practices want “their” PCN to be more successful than those around it, thus justifying the choice of the practice to join it in the first place.

Anyone working in general practice at present understands the pressure that the sector as a whole is under.  When faced with such an existential challenge, there is real value in working together to meet the challenges rather than shifting to a ‘survival of the fittest’ type attitude.

This is perfectly illustrated when considering the respective plight of lions and wolves.  It is estimated there are 20-30,000 lions left in Africa.  50 years ago there were 450,000 lions, a decline of more than 95%.  While historically their numbers had grown, the emergence of man as a predator of lions is the major factor behind their decline.

However, what is astonishing is that the majority of lions are still killed by other lions.  In some prides 80% of the cubs don’t survive.  Either they are killed by other males, or they don’t get enough to eat (they typically eat last in the hierarchy of the pride).  Lions evolved without a predator with an instinct to dominate the savanna from each other, not to share it.

The similar emergence of man as a predator of wolves resulted in the number of wolves declining by about a third.  However, their population is now relatively stable at about 300,000.  Wolves care for each other as individuals.  They form friendships and nurture their own sick and injured.  Pack structure enables communication, the education of the young, and the transfer of knowledge across generations.  The older wolves, as more experienced hunters, share hunting strategies and techniques with younger wolves, passing down knowledge from one generation to the next.

While lions collectively struggle because of their individual desire for dominance, wolves succeed because they cooperate and support each other.

The lessons for newly formed PCNs are clear.  Do we build PCN governance structures to ensure the most successful practices aren’t negatively affected by the practices that are not performing as well, or is the aim to support all practices regardless of their starting point, and to help those most in need to improve?  Do we share information, ideas, resources, expertise with other PCNs, or do we keep it to ourselves and leave other PCNS to work it out for themselves?  Do we collaborate with other PCNs to create a strong voice for general practice, or do we let inter-practice and inter-PCN disputes weaken our collective stance, as we argue against each other in public so that others can simply ignore the general practice position?

We should judge PCNs not on how they are performing relative to other PCNs, with metrics devised by the system, but on how well they are supporting their member practices, and the extent to which they are enabling general practice to thrive.  The more both practices within a PCN work collaboratively together, and PCNs work collaboratively together with each other, the more general practice will thrive.  It may even be we get to a place where “the strength of the PCN is the practice, and the strength of the practice is the PCN”!

What is your Primary Care Network’s Purpose?

I was sitting in a nascent PCN’s meeting recently, and watching the practices grapple with the challenges of forming a new network, and at the same time thinking of the quite common advice for PCNs to establish a common purpose.  Sitting there, I imagined saying to the practices that what they needed to do was spend time identifying and agreeing a common purpose, and equally visualised my rather speedy subsequent removal from the room.

I understand that forward thinking practices can get to the place of considering what the purpose is of their shared network.  But for most practices the current challenges are agreeing who will be in the network, who will be the leader, how they will make decisions, who will hold the money, and how they will deliver extended hours.  There is no time (or patience) for esoteric questions about purpose, when there is so much that needs to be done in the little time they have together.

Does that therefore mean that those PCNs who have not explicitly addressed the question do not have a purpose?  Or is the (unspoken) purpose enabling practices to do what they need to do to fulfil the contract, and receive the funding and resources to which they are entitled?  If there is no purpose at all, you could argue practices would have rejected the Network Contract DES.

Framed more positively, is, then, the (unspoken) purpose of PCNs to increase investment in, and the sustainability, of general practice?  Is it to reverse historic underinvestment and enable general practice to emerge from its current crisis?  Are PCNs in fact a “lifeboat” (as it was termed at a recent Nuffield Trust event) for general practice?

I co-authored a book entitled the Future of General Practice, in which we explored what practices who had emerged from the current crisis had done.  Broadly speaking they have introduced new roles, found ways of working at scale, and began to form partnerships with other providers in the wider system – all elements of the new PCNs.  Like them or loathe them, there is no doubt PCNs represent an opportunity for general practice to create a more sustainable future for itself.

Is it ok for the purpose of PCNs to be first and foremost about investment in and the sustainability of general practice?  As we discussed last week, the system wants PCNs to be about the integration of general practice with the wider system.  And can anything in the NHS be about anything other than improving outcomes for patients?

I would argue that if the system partners with a general practice that is essentially broken, the benefits will be limited.  And if supporting general practice is the way to improve outcomes for patients, then it is perfectly reasonable for that to be its primary goal.  Where general practice is in crisis, the purpose of PCNs needs to be to support them out of it.  Integration with the wider system, and improved outcomes for patients, will be happy bi-products of this primary purpose being fulfilled.

The challenge for PCN leaders is to be clear on the purpose of their PCN.  While the discussion might not explicitly have been had, GP leaders will know why their colleagues are turning up and what their expectations are.  I think there is actually real value in these leaders making the implicit explicit, and using this positive articulation of exactly what it is practices are doing together to give energy to the PCN from member practices.  Ultimately, practices, the wider system and patients will all benefit from this.

Page 57 of 89
1555657585989



