Who is to blame for the current crisis in general practice?

Who is to blame for the current crisis in general practice? NHS England? The government? Jeremy Hunt? Workforce planners? The bankers because of what happened in 2008? Millennials, because of their demand for instant-everything? Somebody else?

Whose job is it to sort out the crisis that general practice is in? Is it the same people whose fault the crisis is in the first place? Or is it Simon Stevens, NHS England, Jeremy Hunt, the government, or maybe even the BMA and the national general practice organisations?

These will not be unfamiliar questions for GPs. The injustice of the current situation pushes them into almost constant consideration. But focussing on them does not help individual GPs and practices find a way through the challenges they have to contend with on a day to day basis.

I am sure many readers will have at some point come across Stephen Covey’s book, “The Seven Habits of Highly Effective People”, first published in 1989 with over 25 million copies sold. Within the very first habit that Covey identifies of very successful people (“be proactive”), he introduces the Circle of Concern and the Circle of Influence.

The Circle of Concern contains all those things we focus our energy and efforts on over which we have little or no control, such as the weather, Iran’s nuclear programme, or national debt. For GPs it includes working out who to blame for the crisis afflicting the profession, and considering how much of the soon to be announced additional NHS funding will make it to front line general practice.

The Circle of Influence contains all of those things that we can directly control or influence, such as our actions, our behaviours, our family and our colleagues. For GPs this includes their own individual practice.

The habit successful people have, according to Covey, is focussing their energy and effort in the Circle of Influence where they can make a difference, and not wasting it in the Circle of Concern over which they have little or no influence.

I see this difference regularly in GP practices. The factors causing the crisis are outside of the control of practices. The local response to them, however, is within their control. Some GPs and practices focus their energy on the former, and some on the latter.

The barrier that stops many GPs focussing on the Circle of Influence and the changes they can make is this question of who is to blame for the challenges the practice faces, and whose job it is to sort it out. If it is not my fault, and I am essentially a victim of a system failure, why should I be the one who has to sort it out? Letting go of the unfairness of the situation is far easier said than done.

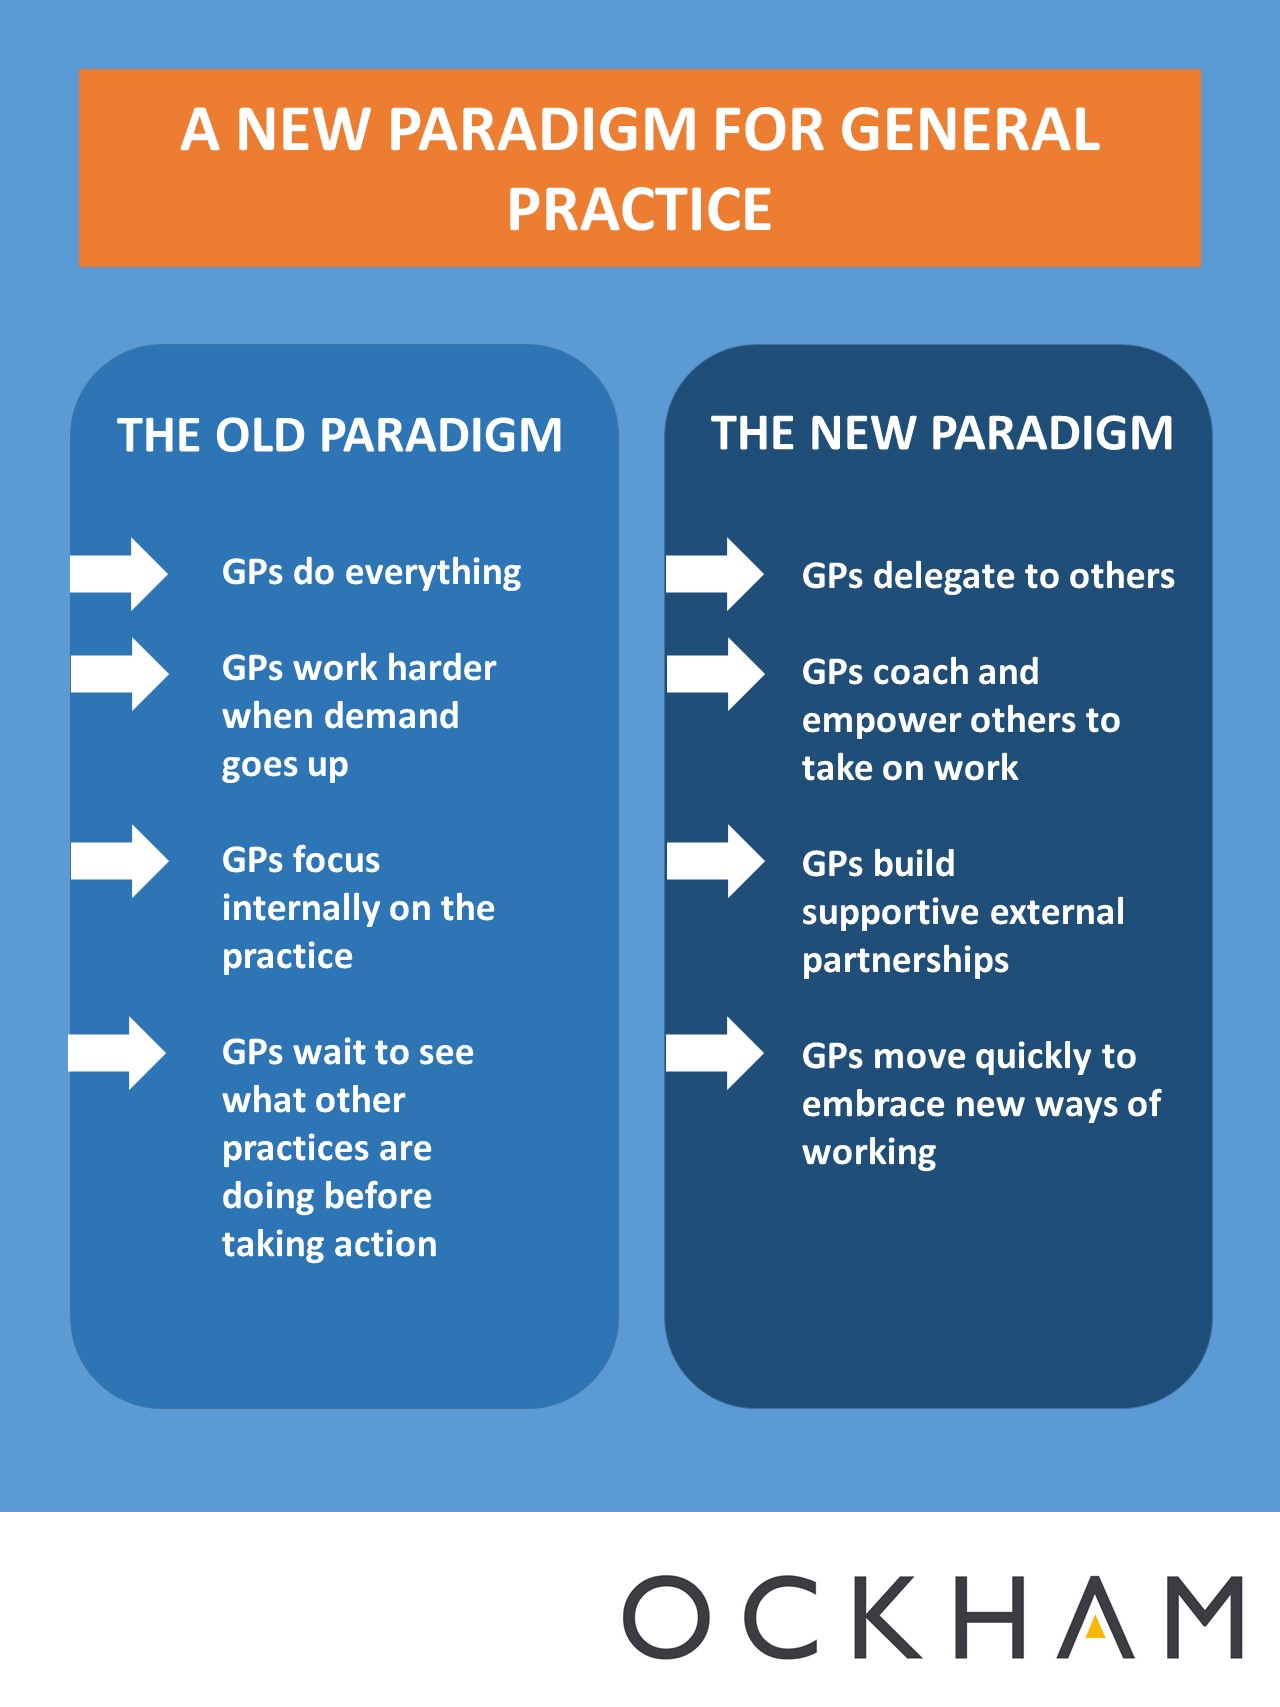
But the practices who are thriving and doing best in the current environment are those focusing their energy within their Circle of Influence; the ones who are looking at how their own behaviours and actions and relationships can influence and change the current situation for the better. They have not waited to react to changes that others will make at a national or policy level, but have taken things into their own hands.

I recently visited Thistlemoor Medical Centre in Peterborough. The majority of their local population do not have English as a first language, and recruiting GPs has been a longstanding problem. But they have focussed on what they can control, and have created a really innovative model so that instead of relying on Language Line they have trained HCAs recruited from the local community to both interpret and take work off the GPs (you can find out more about their model in an upcoming episode of the General Practice Podcast). The practice is thriving and continues to grow at well over 1,000 patients a year.

In Plymouth three practices merged in 2014 to form Beacon Medical Group, and they created a new multidisciplinary team to manage the on-the-day demand. Since then, in the midst of a really challenging local environment, the practice has grown and continued to prosper.

These are just a couple of examples, and there are many across the country. What they have in common is that local GPs focussed on what they could control not what they could not, and took action. They did not waste their energy assigning blame or hoping for national solutions, but instead channelled their efforts within their own Circle of Influence to change the direction in which they were heading.

Thinking about who is to blame for the crisis in general practice is considering the wrong question. It is operating in the wrong circle. The real question to consider is what can I do, what can I influence, to create a vibrant and positive future for my practice, and to focus all my energy and efforts there.


The impact of the new models of care on general practice

“Remind me what they are again” the GP responded. I was asking what his thoughts were on the new models of care. I jogged his memory with a few choice acronyms (MCP, PACS, PCH etc). “Oh those. Hard to say really…”. He trailed off, interest clearly waning, and then visibly winced as he saw the message on his screen indicating the number of patients waiting to be seen.

The concept of new models of care has not really taken off as a driving force for change in general practice since they were first proposed in the five year forward view (5YFV) in 2014. Certainly not within the specific frameworks outlined within that document. Frankly, general practice has been too busy. But some of the principles underpinning the models can be seen in some of the recent developments in general practice.

The relative isolation of GP practices has changed more in the last few years than at any point in its history. Practices are far more prepared to work with each other. We have seen mergers, super-practices, federations and networks proliferate. Practices are also more willing to work with other health and social care organisations, in particular those from community and voluntary sectors. A team based approach is both building resilience and creating a more attractive proposition for incoming staff.

Practices are also far more open to reviewing their governance model. The pressure the partnership model places on individual GP partners has led many to explore other options. There has not been a wholesale move away from the GP core contract in the way that maybe some envisaged when the 5YFV was published, but the desire to retain the “independent contractor” status is no longer as strong as it once was. We may well have only seen the beginnings of the rise of at-scale general practice entities like Modality, Our Health Partnership and Lakeside, as well as acute/primary care collaborations like those in Wolverhampton and Yeovil.

General practice has also shown signs of wanting to tackle the wider determinants of health, rather than simply meeting the ever-increasing presentations of health concerns. There is a dawning realisation that something has to be done to tackle the drivers of demand growth. This sits under much of the primary care home movement, and places like Fleetwood are leading the way in taking this on.

These changes have been framed far more by the challenges the profession is experiencing than by the 5YFV. If I had asked my GP colleague about the impact of the pressures on general practice in recent years, rather than about the new models of care, he would have been much more forthcoming.

But moving away from crisis can only be half a story. We know what we are moving away from, but where are we going? What will be the impact of the new models of care going forward? Do they offer a destination for the journey on which many have already embarked?

The emergence of STPs is the current manifestation of the 5YFV implementation. There is something of a battle around size within STPs, when it comes to integrated care systems. Is the local model to be built around primary care home sized units of 30-50,000 as the focal point of change efforts, driving improvements to health as well as health care in local communities? Or is it to be driven at STP level or acute hospital sized units, with primary care homes operating as sub-localities of sub-localities, languishing at the bottom of the health ecosystem? In many places both are still possibilities, but the window of influence isn’t going to stay open for long.

Much of this depends on voice. There is a challenge for general practice to create a coherent and cohesive voice for general practice as a provider within the STP arena. Some places (like Manchester) have worked hard to create this, but for others the primary care seat is still empty. Without a voice, let alone a unified one, it is hard to see the impact of the new models being a positive influence on the future of general practice, despite the opportunity they represent.

Why is the GP Forward View not working?

It is now two years since the publication of the GP Forward View (GPFV). Do things feel any better? Not for most GPs. In a recent Pulse survey 80% reported their workload had worsened over the last two years. So why has the promised £2.4bn recurrent investment, with all the trimmings alongside, failed to have any impact so far?

Looking back, I wonder what the GPFV was. Was it a strategy document? Not really, because there was no clear sense of direction. A recovery document for a service in crisis? Maybe, although it was written at arm’s length from GPs as providers. I think it was a commissioning plan, or commissioning intentions at a stretch. It was what NHS England, and the CCGs, would do to support a service in crisis. It was also a public, political document designed to demonstrate the concerns of GPs had been heard and were being addressed.

Understanding what the document was gives an insight into why it is not working. The headline investment figure of £2.4bn was an overstated figure. The real five-year investment plan was under £1bn. But the figures were extrapolated back to 2013 (the details are here) to inflate the figure to £2.4bn. Promising more than is going to be delivered is a sure-fire recipe for underwhelming results.

A cynical view of the document is that it was also a very clever way of packaging the extended access agenda to make it palatable to GPs, at a time when many were close to breaking point. While the share of funding for general practice within overall NHS expenditure has not really changed, the challenges of GP recruitment have not been addressed, and workload continues to rise, the one clear “success” of the document is that extended GP access is being introduced across the country. Ask any CCG which of the targets in the GPFV they are most closely monitored on and they will tell you it has been all about access. While the problems in general practice have not been alleviated, the government’s primary agenda for the service is being delivered.

There are some good things in the GPFV. The Releasing Time for Care programme and the work of Robert Varnum on the 10 high impact actions, which I admit I was initially sceptical about, I now think is possibly the most impactful part of the document. Practices changing themselves is the only realistic way out of the crisis, and this programme empowers and enables practices to do this. The support for indemnity looks like it is heading in the right direction, and the funding for new roles such as pharmacists has definitely helped.

But the reality is the workforce crisis persists (1,300 full time equivalent GPs left between September 2015 and September 2017), the workload continues to grow, the capital investment through the elusive ETTF simply has not materialised, and funding remains insufficient. Worse, the rhetoric around the GPFV has put general practice to the back of the queue when further funding is announced, e.g. the chancellor’s pledge of an additional £2.8bn to the NHS at the last budget had nothing earmarked for general practice.

Our collective failure to understand what the GPFV as a document was means we are now left without a clear plan or sense of direction for general practice. We initially thought (wrongly) the GPFV provided this, but what it needed (and what it still needs) is a provider led response to say this is how we will use the commissioner promises made in the GPFV to deliver a new future for general practice, and this is what it will look like. There are enough green shoots out there (the primary care home, the great work of NHS Collaborate, and the 108 episodes of the GP podcast are all testament to that) for this to be possible. But without it, either at a local or a national level, I fear the situation will be worse in 2021 than it was when the GPFV was published.

The Millennial Opportunity for General Practice

I am not a millennial. I am not a baby boomer either. To be honest with you, I don’t really know what I am (although apparently I am part of the “lost generation”). How could this possibly matter? Aren’t they just analytical constructs marketing people have developed to try and categorise different age groups?

Broadly speaking millennials are those currently aged 18-35. The first concrete example of the importance of this generation to general practice has been the startling growth of the GP at Hand service, where the practice of offering video consultations grew by 20,000 in 4 months. 85% of the patients joining were millennials.

So maybe there is something in the “millennials are different” mantra after all. This South African analysis resonates:

“The nature of the digital age is to prioritise speed, convenience, and value. The millennial, being digitally native, is exactly the same. This extends from their interactions online to their experiences in healthcare. Doctors do need to look at ways to adapt their practice to meet these expectations in order to meaningfully connect with their patients. From online bookings to …SMS alerts and online calendars, practices already have a multitude of digital solutions to choose from. It is OK that you make changes incrementally, but it is vital that practices start thinking about ways to increase the convenience and speed of the new doctor-patient process.”

Millennials: Getting to know the Patients of Tomorrow, Healthbridge, South Africa

The consensus is that the number of millennials is about to surpass the number of baby boomers, and the differential between the two will grow in the coming years. It is not only our patients but also our doctors who will increasingly be millennials.

Millennial doctors may well be less a product of a technological age, and more a group affected by the junior doctor dispute, the Bawa-Garba case, and training in a system where both they and their senior role models are struggling to cope. It is hardly surprising they feel unsupported, under-valued, and uninspired.

Add to that the growing rejection of the “deferred life plan”, of putting off what you really want to do for what is expected of you, of the idea of working hard until you are 65 to enjoy the benefits later. This is evident in the conflict between a generation of doctors who accepted intolerable conditions when they were training with a new generation who simply will not.

Lucy Cohen, in her article Why Practices Must Engage Millennials, writes,

“As a business owner, millennial, and employer of millennials, I see how different our lives are to that of previous generations. Expect to see them sitting at their desk for set hours of nine to five? Those days are long gone. And if you want millennials to engage with you, then you need to get on board with that idea. We’ve grown up accustomed to communicating and receiving answers almost instantly. So if your (practice) wants to engage with us, we need you to have systems in place to keep us posted on things.”

What I see in all of this is a tremendous opportunity for general practice. The NHS, and its constituent statutory bodies, is not going to be able to respond quickly to the demands of the new generation. The entrenched culture runs too deep. But general practice is far more agile. Individual practices can find ways of letting go of the past and of creating a new, different future that caters for the changing needs of the patients and the staff coming through the doors.

By strengthening the connection with their local community, by valuing individuals over traditional structures and ways of working, and by embracing the opportunity of technology, general practice can become the destination of choice for millennial doctors. It can also harness the growing engagement of millennial patients in their own health to improve health outcomes.

Understanding the changing needs of millennials is important because understanding the needs of our staff and our patients is important. It is an important place to start as we try and shift our thinking from “how do I get out of this crisis?” to “how do I build a sustainable future for this business?”

I will be exploring this issue in much more detail with a panel of experts this month. Watch out for the podcast episodes of these discussions which we will publish over the summer.

Page 68 of 89
1666768697089