

The Independence of General Practice Series – 1

Ben Gowland introduces an exciting new series from Ockham Healthcare:

In the last couple of years I have written a few articles about the independence of general practice.  The current review of the partnership model being carried out at the behest of government, which is considering what has been the bedrock of general practice for so many years, will inevitably have to consider the issue of independence.  This prompted me to bring together and update what I have produced so far, along with some new thoughts, to create an autumn series of articles on this topic.  Over the course of 5 articles throughout August I will consider the threats to the independence of general practice (from within general practice, from the wider system, and from the review itself), reflect on its importance, and identify what might be needed for it to be preserved.”

In this first blog Ben considers the impact that fewer and fewer GPs choosing to become partners will have on the independence of general practice:

Without GP Partners General Practice will lose its Independence

For me, one of the biggest strengths of general practice is its independence. It contracts with the NHS, but is not part of the monolithic NHS structure. For some this may feel like a technical difference (after all GP practices can still access the NHS pension, and they are funded with taxpayer money) but for someone who has spent 20 years working in the NHS like myself the difference feels much more fundamental.

GP practices are bound by the terms of their contract with the NHS. But within the boundaries of those terms they are free to innovate, make changes, and take whatever decisions they want to improve care for their patients and the working lives of their staff. This is in stark contrast to NHS organisations that are bound by NHS-wide restrictions, ways of operating and approval mechanisms that often stifle innovation and directly impact on culture.

It is now widely accepted that GP practices require more money – whether they are funded directly or through a contract. Moving away from the independent contractor model is not an answer in itself to the challenges facing practices. It will not solve the problems of inadequate funding, insufficient GPs, or growing workload. Independence is not a cause of these problems, but rather is the only reason GP practices have been able to continue the way they have despite the current pressures.

Yet, sadly, the independent contractor model is teetering on a knife’s edge. I visited a practice recently that a year ago was a relatively stable, well-run, 4 partner and 7500 population practice. Within the space of two weeks two of the partners resigned. One was retiring, and one was emigrating to Australia. A few weeks later a third declared they were also resigning as they wanted to become salaried. This left a single GP, who had neither the skills nor the desire to be the sole partner of the practice. She wrote to the CCG informing them of the situation and declared that if a solution was not found she would be forced to hand back the list.

This scenario and others like it are being played out throughout the country. The inability to recruit GP partners is rising to the top of the challenges facing GP practices today. Every resignation of a GP partner creates panic within practices, a sense of being trapped, and a fear of being the one left carrying the costs of closure.

The recent push to secure 5000 new GPs, whilst unlikely to be achieved, has brought new GPs into the profession. But many of these GPs are choosing part time or portfolio careers. The competition for new GPs is pushing up the pay for salaried GPs. The new extended access and A&E based services provide well-paid, flexible alternatives for new GPs, further increasing the challenges of recruitment for practices.

The risk is that, unconsciously, we are creating a system that rewards salaried GPs and punishes GP partners. The number of “zombie practices”, where the salaried GPs earn more than the partners, is reportedly on the rise. By not intervening, general practice as a profession is risking its independence. Without GP partners, there are no businesses that can deliver against the contracts, no practices as we know them today. The NHS will have to directly deliver the service. Once independence is gone, it will never be regained.

I do not believe GPs, even new GPs, by not choosing to be partners are choosing for general practice to relinquish its independent. But I believe that is exactly what is happening below the surface, unnoticed; not as a conscious decision or policy intent, but as an unintended consequence of the way the system now operates (“every system is perfectly designed to get the results it gets” etc.) We have not paid this dilemma enough attention, and must take urgent action before it is too late.

Nigel Watson is leading a review of the GP partnership model. My sense is we need to make becoming a GP partner more attractive. We must provide more training and preparation for GPs who do want to take up the challenge of becoming a partner. We must cherish the independence of general practice, and help the future generation of GPs understand not only the freedom it provides but also what will be lost without it. With or without the review, unless we take action now, general practice will lose its independence.

Funding GP Networks

The general consensus appears to have fallen on integrated care systems and primary care networks as the way forward. CCGs have been instructed to encourage every practice to be part of a primary care network, which are to cover populations of (roughly) 30-50,000, and as a result a plethora of these new entities are now developing.

Here is a question: where should the funding for the management of these primary care networks come from?

We may not be convinced that another layer of management in the NHS is what is needed, but if the mantra of the day is primary care networks, and the point of them is to enable core general practice to partner effectively with other providers within an integrated care system, then some management function is going to be required.

What are the options?

1.Use the management margin gained from the delivery of additional services.

Traditionally this is how GP federations have made themselves sustainable. In some places this is the assumed mechanism for developing the management funds for these new organisations. The problem is that the networks are expected to represent the delivery of core general practice, not simply the delivery of the (small) range of new services they may provide. This method creates an incongruence between what the network does and the voice it is supposed to have. It also serves to inflate the management costs they have to charge for any service delivery, which is likely (at some point) to make them uncompetitive.

2.“Investment” by GP practices.

In this model GP practices chip in anything up to £2 per head of practice population. This ensures the network function has a clear sense of ownership from its member practices, and that it speaks on their behalf. The challenge comes here with the underfunding of general practice in recent years. Establishing the networks becomes another drain on GP practice resources, at a time when many practices simply do not have the spare financial capacity. As a result, many practices will choose to pass when the opportunity to directly fund the new networks comes along.

3.GP Transformation Funds.

The GPFV is investing a considerable amount of funding to enable “transformation” in/of general practice. Some STP areas are using the transformation funds to support the establishment of GP networks with appropriate management. This is a sensible starting point, but really is deferring the question of where recurrent funding will come from, rather than answering it (i.e. what happens when the non-recurrent transformation funding runs out?).

4.Additional Funds for the GP contract.

Essentially, a model could be introduced whereby additional funding is given to every practice through their contract, for them to use to fund the management resource required for primary care networks. A similar approach was used in practice based commissioning days when practices in many areas received an enhanced service for practice based commissioning, although then they could choose to use it themselves or pool it to create a shared function.

The benefit of this approach is it ensures GPs retain ownership of the management function because even if it is “pass-through” funding, it comes from the practice. This creates the accountability between the network and the practices that is required for them to be successful. The downside is that local disputes and disagreements make local arrangements hard to pin down and sustain over a period of time – just look at the blood, sweat and tears it took to tie down CCG configurations.

5.Transfer of some CCG management allowance

The final option (that I can think of) is the transfer of some of the management funding that sits within CCGs to these new networks. CCGs as member organisations at some stage in the move away from the commissioner/provider split are going to cease to exist, and the natural replacement for groups of practices looking to work together to improve population health (although this time as providers) is going to be primary care networks, so it seems a relatively logical move. It may also serve to stop the shedding of the huge amount of GP leadership talent that CCGs have uncovered.

This would be a recurrent resource, but the downside would not only be the lack of ownership from practices that this move may generate, but also a reinforcement of an unease held by some GPs that primary care networks are the next iteration of PCGs/PCTs/CCGs.

It will be interesting to see where this ends up. It is important that general practice fights hard against the result defaulting to option 1, which in the end will serve no-one, and put unrealistic pressures on network leaders. I suspect we will find ourselves in some form of amalgam of option 3 (to get things started) and option 4 or 5 – but with the proviso that additional recurrent funds build on and develop whatever was established in the start-up phase to prevent huge backwards steps.

The Tyranny of Governance

There is something difficult, elusive even, about the concept of governance. It should be straightforward. According to the universal fount of all knowledge (Google) the definition of governance is, “the action or manner of governing a state, organisation etc.” Yet somehow in the NHS, governance has drifted into becoming a stick managers wield over clinicians to drive compliance.

Am I overstating it? I am not sure. The first time I really saw evidence of this was when CCGs were first formed. Keen, eager and green, groups of GPs worked together determined to use NHS money to make a difference to local populations. But then these fledgling organisations were subjected to an “authorisation” process, where the focus was on governance and the ability of CCGs to operate as stewards of public money.

Whatever your views on the rights and wrongs of the authorisation process, the result of it was that it sucked the life and spirit out of nearly all of the CCGs. The model constitution, non-executives, multiple committees (etc. etc.) all contrived to create organisations too unwieldy to make any real change happen, to diminish trust between the organisation and its member practices, and to sap any sense of organisational pride or identity.

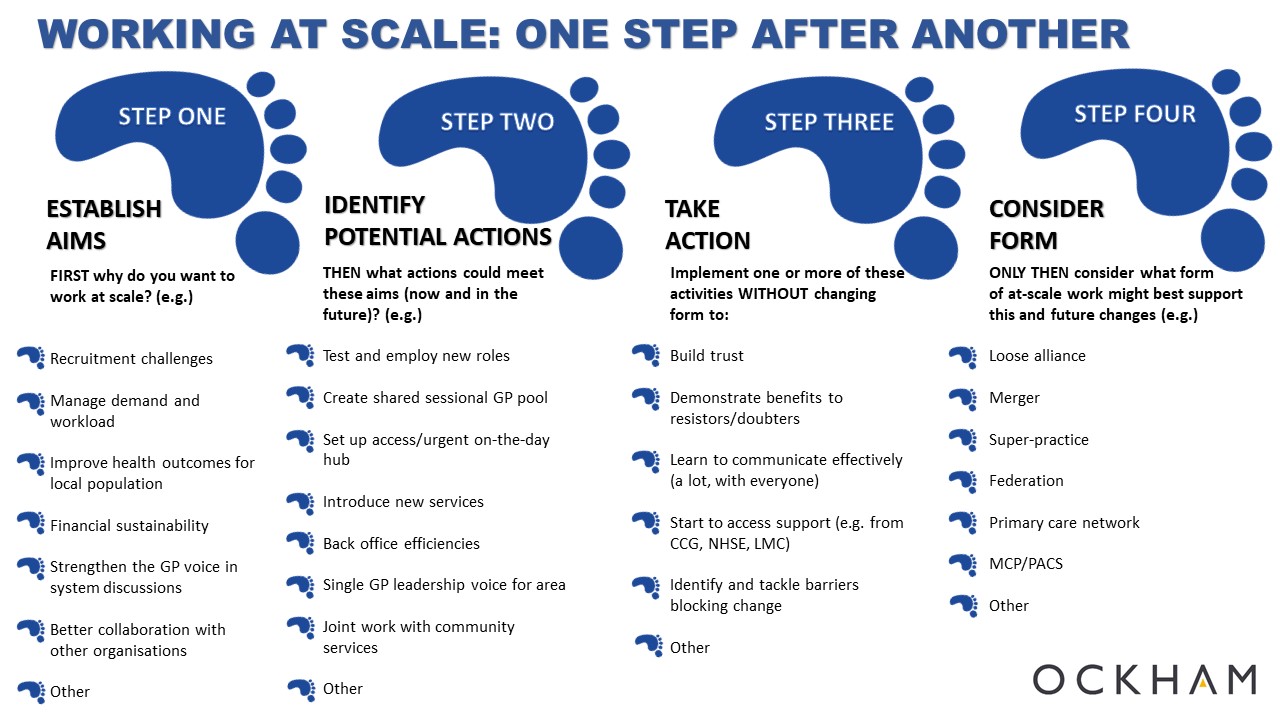
Last week we published our four step guide for practices working at scale. The real point of this was to encourage practices wanting to work at scale to think about why they wanted to work together and what they wanted to do before getting bogged down in questions of governance.

Don’t get me wrong, governance is important. But it is not more important than having a clear purpose for the at-scale general practice organisation, or more important than working out the guiding principles that will determine how the organisation will operate (its values). It is not more important than building trust between the new at-scale entity and the member practices, or more important than achieving the goals the organisation has set itself. Focussing on these things makes good governance an enabler, rather than governance existing for governance’s sake.

In the days when CCGs were being established, the key cry from practices was that it “did not become like the PCT”. Now the concern from practices about the development of new at-scale general practice entities is that they “don’t become like the CCG”. Yet the pressure “to have good governance” is often forcing some of these newly-emerging organisations down the same route. This is the tyranny of governance.

But things can be different this time. The cycle can be broken. At-scale general practice organisations are not statutory bodies in the same way that CCGs are. They do not have to hold population-based budgets (which will take them down the CCG route), and it is perfectly feasible for them to partner with other organisations (with the required governance) to enable that to happen. They can be whatever the member practices want them to be.

This means there is no ‘right’ model of governance for them. There is no checklist they have to adhere to.   Appropriate governance will depend on exactly what it is they are trying to achieve and do.

New at-scale GP organisations have choices. First they must determine why they exist, then decide what they want to do and the way they want to do it, and finally choose what governance they need to enable them to do the things they want to do in the way they want to do them. Governance in its place is an amazing enabler, but out of place can create a fast track to failure.

Working at scale – the right way to proceed

Many practices are considering the benefits of working at greater scale. But, from our experience at Ockham, we see so many approaching it from the wrong direction; by considering what form this expansion will take before even reaching agreement on why they are seeking to get bigger. So we have put together a simple and helpful guide on the steps practices should take to help them successfully navigate this journey.

Do GPs want to work at scale?

When I was about 5 years old my brother and I became supporters of Liverpool Football Club. No-one told us we had to. Our parents were not football fans. We did not have to sit in a class to learn about Liverpool Football Club, or pass an exam before we could watch them play. No-one forced us to learn the names of all the players, or their shirt numbers, or the endless statistics from the previous decade. We learnt about the club because we were passionate about it which created our energy and enthusiasm to find out as much as we could, whenever we could, and to pester our father constantly to take us to matches.

Whilst not a football fan, my mother was a catholic. So when we were the same age every Sunday she used to make me and my brothers go to church. We never asked to go, and we went because we had to. We didn’t pay attention, got out of going whenever we could, and spent our time when we were there daydreaming about Anfield and whether Liverpool would win when they next played, as well as generally causing trouble. Eventually, we made life so miserable for my mother that she stopped making us go.

Now I am older, things are not much different. I spend my time doing the things I am passionate about and enjoy doing. There are some things I have to do (chores, shopping etc.), but, as my wife will no doubt attest, I do them as quickly as I can (or try and get out of them!) so that I can focus my efforts on the things that matter to me.

My brother is the same. In fact, we all are. We all want to spend time doing the things we want to do and care about, and avoid doing things we are doing because we have to. GPs are no different. Most GPs want to spend their time in the practice, focussing on making a difference to patients and the things that matter, not doing the things they feel they have to do (but hate) like preparing for a CQC inspection, or attending yet another CCG meeting.

For GPs, where does operating at scale fit in to the spectrum, where “doing it because we have to” is at one end, and “doing it because we are passionate about it and the difference it can make” is at the other?

Looking around the country, it varies.

Some GPs are really passionate about operating at scale. They believe it is key to the sustained future of the profession, to ensuring GPs have a strong voice around the system table and to giving them the best chance of making a difference to the lives of their patients. They seemingly work 24 hours a day on making it happen, putting all their spare time into it, and do so with boundless energy.

But many GPs are doing it because they feel they have to. They feel the weight of system pressure pushing them in that direction, and go along with it because even if they recognise there is some logic to it, their heart is in small, independent general practice. Unsurprisingly, they rarely turn up to meetings, they contribute only what they have to, and are often negative and disruptive.

GPs working at scale because they want to, not because they have to, is what will create the energy to make something great happen. It is what already differentiates those really successful examples of working at scale from the rest. Getting the majority of your colleagues to agree to doing something they do not believe in is storing up problems for the future. Jumping into a federation or a network without even knowing why is a mistake, because you won’t invest of yourself in it.

Spend time on why. Spend as much time as it takes to generate energy for a movement, and only then move forward. That investment of time will repay itself multiple times in the future, because it won’t feel like (your equivalent of) going to church, but instead like going to Anfield!

Page 66 of 89
1646566676889

